
Final CY 2027 HH PPS Payment Update Rule Posted
Final CY 2026 HH PPS Payment Update Rule Posted
The final Calendar Year 2027 Home Health Prospective Payment System (HH PPS) Rate Update; Requirements for the HH Quality Reporting Program and the Expanded HH Value-Based Purchasing Model; Medicare Provider Enrollment, Durable Medical Equipment (DME), and DME, Prosthetics, Orthotics, and Supplies (DMEPOS) Policies was posted on the Federal Register Public Inspection desk on 11/4/2026. The final rule’s general effective-date provision states that, except for specified HH PPS, HH QRP, and § 484.245 provisions, the regulations are effective 60 days after the rule is filed for public inspection at the Federal Register. The document was approved on October 28, 2026, and scheduled for Federal Register publication on November 9, 2026; based on the stated timing, this is December 28, 2026.
Please note there are items in this final rule that apply to Medicare-certified hospice providers.
Providers are strongly encouraged to review the rule in its entirety as this is only a summary of the content. Here are the highlights of the final rule.
Note: The only Part 484 regulatory amendments are HH QRP administrative and reporting-process changes in § 484.245; the substantive HHA CoPs remain unchanged by this final rule.
Payment Update
Final CY 2027 updated rates include a CY 2027 home health payment update of 2.1% ($365 million increase) and an estimated 0.3% increase that reflects the updated fixed dollar loss (FDL) amount ($50 million increase). CMS estimates that Medicare payments to HHAs in CY 2027 would increase in the aggregate by 2.4%, or $415 million, compared to CY 2026, based on the finalized policies.
CMS is also applying a 3.0% temporary behavioral adjustment to the CY 2027 national standardized 30-day payment rate. This is a separate adjustment intended to recover historical PDGM-related overpayments. CMS declined commenters’ requests to abandon the reduction. It maintains that applying the adjustment now reduces the need for a larger adjustment later.
CMS does not propose any new permanent behavioral adjustment, noting that most PDGM-related behavioral changes had already stabilized by 2022.
Final CY 2027 National, Standardized 30-Day Period Payment Amount
| CY 2026 National Standardized 30-Day Period Payment Without Temporary Adjustment | CY 2027 Case-Mix Weights Recalibration Neutrality Factor | CY 2027 Wage Index Budget Neutrality Factor | CY 2027 HH Payment Update Factor | CY 2027 National, Standardized 30-Day Period Payment Without Temporary Adjustment | Temporary Adjustment Factor | CY 2027 National, Standardized 30-Day Period Payment With Temporary Adjustment |
| $2,101.26 | 1.0047 | 1.0009 | 1.0210 | $2,157.41 | 0.9700 | $2,092.69 |
The CY 2027 national standardized 30-day period payment rate for an HHA that does not submit the required quality data will be updated by 0.1 percent (the final CY 2027 home health payment update percentage of 2.1 percent minus 2 percentage points)
Final CY 2027 National Per-Visit Payment Amounts
| HH Discipline | CY 2026 Per-Visit Payment Amount | CY 2027 Wage Index Budget Neutrality Factor | CY 2027 HH Payment Update Factor | CY 2027 Per-Visit Payment Amount |
| Home Health Aide | $80.12 | 0.9999 | 1.0210 | $81.79 |
| Medical Social Services | $283.64 | 0.9999 | 1.0210 | $289.57 |
| Occupational Therapy | $194.74 | 0.9999 | 1.0210 | $198.81 |
| Physical Therapy | $193.42 | 0.9999 | 1.0210 | $197.46 |
| Skilled Nursing | $176.96 | 0.9999 | 1.0210 | $180.66 |
| Speech-Language Pathology | $210.25 | 0.9999 | 1.0210 | $214.64 |
For HHAs that do not submit the required quality data for CY 2027, the final home health payment update percentage is 0.1 percent (2.1 percent minus 2 percentage points).
Request for Information – Home Health Specific Wage Index
CMS acknowledged in the proposed that the hospital wage index may not accurately reflect the labor costs faced by home health agencies. They asked for feedback on whether alternative data sources could be used to create a wage index that more closely reflects the home health workforce and home health operating environment. Specifically, CMS is considering whether future wage index calculations could incorporate:
- Bureau of Labor Statistics (BLS) occupation-level wage data.
- Home health cost report data.
- Other methodologies that better capture local labor costs for home health providers.
The comment themes CMS received are summarized below:
- Hospital wage data may not accurately reflect home health labor costs
- Support for developing a home health-specific wage index
- Workforce recruitment and retention costs vary significantly by geographic market
- Concerns about rural versus urban labor-cost differences
- HHAs cannot benefit from hospital geographic reclassification and rural-floor policies
- National budget neutrality can still create significant payment disparities for individual HHAs
- Need for more accurate home health-specific wage and labor-market data
- Concerns about payment stability and year-to-year wage-index fluctuations
For CY 2027, CMS continued using the hospital wage index as the basis for home health payments and will continue applying the existing 5% cap on annual wage index decreases, which protects agencies from significant year-over-year payment reductions due to wage index changes.
Annual PDGM Recalibration
For CY 2027, CMS continues its annual recalibration of the Patient-Driven Groupings Model (PDGM) using the most recent available claims data. The recalibration is intended to keep case-mix payments aligned with current patient characteristics and resource utilization. Key CY 2027 updates include:
| PDGM Update | CY 2027 Details |
| Case-mix weights | Recalibrated using CY 2025 claims data, with a 1.0047 case-mix budget-neutrality factor. |
| Functional impairment | Functional points and impairment levels were updated based on CY 2025 data. |
| Comorbidity adjustments | CMS finalized 22 low-comorbidity subgroups and 103 high-comorbidity interaction subgroups. |
| LUPA thresholds | Updated for CY 2027, with thresholds decreasing by one visit for 10 case-mix groups and increasing by one visit for one group. |
Home Health Quality Reporting Program Updates
CMS finalized changes intended to put OASIS and HHCAHPS on the same calendar-year framework for determining compliance with the HH QRP Annual Payment Update requirements, along with changes to associated submission deadlines.
- Alignment of OASIS and HHCAHPS Reporting Periods
- Finalized aligning the reporting periods for the Outcome and Assessment Information Set (OASIS) and the Home Health Care Consumer Assessment of Healthcare Providers and Systems (HHCAHPS) survey with the calendar year.
- OASIS Submission Deadlines
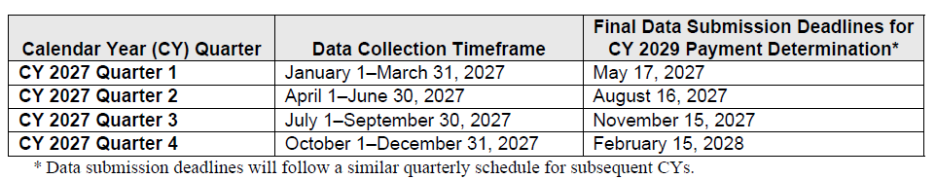
- CMS finalized the proposal as proposed, beginning with the CY 2027 Home Health Quality Reporting Program. OASIS data must be submitted by the 15th day of the second month following the end of each calendar quarter. This means that Providers will have less time after each quarter to review, correct, and submit OASIS data.
| Reporting quarter | Final OASIS submission deadline |
| January 1–March 31 | May 15 |
| April 1–June 30 | August 15 |
| July 1–September 30 | November 15 |
| October 1–December 31 | February 15 of the following year |
Data Collection Timeframe And Data Submission Deadlines for OASIS Assessment Data Affecting The CY 2029 Payment Determination
- HH QRP Measure Concepts Under Consideration for Future Years – Request for Information (RFI)
CMS did not finalize new HH QRP measures from this RFI. This was a request for stakeholder feedback to inform potential future measure development and rulemaking. Support exists for developing person-centered ACP measures emphasizing meaningful conversations over documentation. The comments received by CMS generally centered on these themes:
- Support for meaningful, patient-centered measures that reflect outcomes important to home health patients and caregivers.
- Concern about increased administrative burden, particularly if new measures require additional OASIS items or data collection.
- Preference for measures using existing data sources, including claims, and existing OASIS data, whenever possible.
- Measure alignment across CMS programs, including better coordination between the HH QRP and expanded HHVBP Model, to reduce duplication and competing requirements.
- Need for appropriate risk adjustment so agencies caring for medically complex or socially vulnerable populations are not disadvantaged.
- Importance of testing and validation before new measures are added to the HH QRP.
- Concern about measure proliferation, with commenters encouraging CMS to prioritize a smaller set of actionable measures that clearly improve quality and patient outcomes.
- Interest in measures that better capture care transitions, patient safety, functional outcomes, and the patient/caregiver experience.
Stakeholders were generally receptive to continued improvement of the HH QRP, but emphasized measure relevance, alignment, appropriate risk adjustment, and minimizing additional provider burden.
Medicare Provider Enrollment
CMS finalized several Medicare provider-enrollment decisions as part of its ongoing efforts to combat fraud, waste, and abuse. Most of these provisions apply to all provider types enrolled in the Medicare program and are intended to reduce improper Medicare payments and protect beneficiaries. The final revocation and denial authorities address provider noncompliance and actual and potential fraud, waste, and abuse, and allow CMS to target improper activity by those who own or operate Medicare providers. The provisions include, but are not limited to, the following:
- New denial and revocation grounds: CMS finalized several additional bases to deny or revoke Medicare enrollment and expanded existing grounds, including certain misdemeanor convictions involving sexual assault or financial misconduct within the prior 10 years when CMS finds them detrimental to Medicare and its beneficiaries.
- High-risk geographic areas: CMS may revoke enrollment when a provider or supplier’s location is in a limited geographic area with an excessive concentration of providers or suppliers that presents a high risk of fraud, waste, or abuse.
- HHA, hospice, and DMEPOS ownership compliance: CMS finalized a new authority to deny or revoke Medicare enrollment when an HHA, hospice, or DMEPOS supplier does not comply with the applicable change-in-majority-ownership (CIMO) rules.
- Hospices, home health agencies (HHAs), and suppliers of durable medical equipment, prosthetics, orthotics, and supplies (DMEPOS) must re-enroll in Medicare as a new provider and undergo a survey or accreditation if they experience certain changes in majority ownership.
- For HHAs and hospices under § 424.550(b), and DMEPOS suppliers under § 424.551, a non-exempt majority ownership change occurring within 36 months of the entity’s initial enrollment or most recent CIMO generally requires the entity under its new majority ownership to:
- Enroll as a new Medicare provider or supplier;
- Undergo a new State survey or accreditation for an HHA or hospice; or
- Obtain new DMEPOS accreditation for a DMEPOS supplier.
- For HHAs and hospices, the existing provider agreement is terminated and does not transfer to the new majority owner.
- For HHAs and hospices under § 424.550(b), and DMEPOS suppliers under § 424.551, a non-exempt majority ownership change occurring within 36 months of the entity’s initial enrollment or most recent CIMO generally requires the entity under its new majority ownership to:
- CMS may deny or revoke enrollment when these entities do not comply with the applicable change-in-majority-ownership requirements.
- CMS states that the policy is intended to prevent ownership “flipping” and ensure complete screening of new owners before they can bill Medicare
- Hospices, home health agencies (HHAs), and suppliers of durable medical equipment, prosthetics, orthotics, and supplies (DMEPOS) must re-enroll in Medicare as a new provider and undergo a survey or accreditation if they experience certain changes in majority ownership.
- Hospice reactivation: A hospice whose billing privileges were deactivated must obtain a State survey or accreditation before reactivation, aligning this requirement with the existing HHA policy.
- Retroactive revocations expansion: CMS expanded the circumstances in which it may assign a retroactive effective date to a provider or supplier revocation by finalizing a policy to make all revocation grounds retroactive. Under current regulations, certain Medicare enrollment revocations become effective prospectively, 30 days after CMS or the CMS contractor mails notice of revocation to the affected provider or supplier; other revocations take effect retroactively to the date noncompliance began. The finalized policy is intended to help CMS recover monies paid to noncompliant providers and ensure taxpayer money is paid only to legitimate, compliant providers.
- CMS finalized a 15-calendar-day deadline for submitting pre-revocation claims, measured from the date of the revocation letter. Finalized requirement: 42 CFR § 424.535(h):
- All revoked providers and suppliers except HHAs: Must submit all claims for items and services furnished before the revocation effective date within 15 calendar days of the date of the revocation letter.
- Revoked HHAs: Must submit claims within the same 15-calendar-day period for services furnished before the later of:
- Reapplication bars: CMS may impose a reapplication bar of up to 10 years regardless of the specific enrollment-denial reason, rather than only when false or misleading information was submitted.
- Program or license suspension/termination: CMS currently may deny or revoke enrollment if a provider has a suspended or revoked license in another state or is suspended or revoked from Medicaid or another federal healthcare program. CMS expanded this authority to include similar suspensions or revocations involving the provider’s owners or managing employees or organizations.
Enrollment definition updates – finalized:
| Definition | Finalized Change |
| Managing Employee | A general manager, business manager, administrator, director, or other individual that exercises operational or managerial control over, or who directly or indirectly conducts, the day-to-day operation of the provider or supplier, either under contract or through some other arrangement, whether or not the individual is a W-2 employee of the provider or supplier. For purposes of this definition, this includes not only a hospice or skilled nursing facility administrator and a hospice or skilled nursing facility medical director but also any of the following: (i) Medical directors other than skilled nursing facility and hospice medical directors. (ii) Clinical directors. (iii) Departmental heads (for example, a hospital’s chief of cardiology). (iv) Supervising physicians (not simply those at independent diagnostic testing facilities). (v) Nursing directors. (vi) Alternate administrators. (vii) All other clinical personnel not listed in paragraphs (1)(i) through (vi) of this definition who meet the “managing employee” definition. |
| Final Adverse Action | Misdemeanor conviction. A conviction of a Federal or State misdemeanor related to sexual assault or financial misconduct within the past 10 years preceding enrollment, revalidation, or reenrollment. |
| Operational | Operational means (as applicable, based on the type of facility or organization, provider or supplier specialty, or the services or items being rendered) the provider or supplier meets all of following requirements: (1) Has a qualified physical practice location. (2) Is open to the public for the purpose of providing health care related services, which includes, but is not limited to, all of the following: (i) The provider’s or supplier’s location is fully accessible to all patients and lacks safety hazards. For purposes of this paragraph (2)(i), accessible means– (A) The provider or supplier is located in an area and a building that patients can enter with reasonable ease; and (B) The location is compliant with all federal Americans with Disabilities Act regulations and all applicable and equivalent state and local laws. (ii) The provider’s or supplier’s hours of business are sufficient to regularly serve patients. (iii) Medicare beneficiaries can contact and locate the provider’s, or supplier’s location based on publicly available information (for example, the Internet). (3) Is prepared and able to submit valid Medicare claims. (4) Is properly staffed, equipped, and stocked (as applicable, based on the type of facility or organization, provider or supplier specialty, or the services or items being rendered,) to furnish these items or services. This includes, but is not limited to, the following: (i) Provider or supplier staff must be qualified (such as licensed or certified if required under state law) to perform their health care-related functions. (ii) Equipment must be functional, appropriate for the services and items the provider or supplier intends to furnish, and in sufficient quantity to provide these items and services. (iii) Appropriate medications for the services and items the provider or supplier intends to furnish and in sufficient quantity to provide these items and services. (5) Has adequate written policies and records regarding its operations, such as, but not limited to, procedures for patient care, patient safety, medical and patient recordkeeping, and general administration. |
| Affiliation | Affiliation means, for purposes of applying § 424.519, any of the following: An interest in which an individual or entity – or any of its owning or managing employees or organizations — exercises operational or managerial control over, or directly or indirectly conducts, the day-to-day operations of another organization (including, for purposes of this paragraph (3), sole proprietorships), either under contract or through some other arrangement, regardless of whether or not the managing individual or entity is a W-2 employee of the organization. Any marketing, business, fulfillment, financial, or managerial relationship, whether direct or indirect (including, for example, common use of the same organization to perform these services) |
The final rule also deleted the five-year limit in § 424.519(b): CMS may request disclosure of an affiliation a provider or supplier “has or has had,” replacing “has or, within the previous 5 years, had.”
Qualified Practice Location
CMS finalized the proposed operational and signage requirements without modification, except for a technical correction restoring the word “physical” in “qualified physical practice location.” The detailed requirements are tied to what constitutes a legitimate practice location and the definition of “operational” and related enrollment requirements. Rather than simply having an address on file, providers and suppliers are expected to maintain a qualified practice location that demonstrates actual operational capability.
| Requirement | Description |
| Qualified Practice Location | Providers must operate from a legitimate location capable of furnishing healthcare services. |
| Patient Accessibility | The location must be fully accessible to all patients and lack safety hazards. “Accessible” means: – The provider or supplier is located in an area and building patients can enter with reasonable ease; and – The location complies with federal ADA regulations and all applicable equivalent State and local laws. – CMS clarification: “Area” means the immediate vicinity, such as a parking area or multi-building complex, not distance from a beneficiary’s home. Security locks or personnel are allowed; the relevant question is whether a patient can enter once access is granted. |
| Open and Available to the Public | Being operational requires being open to the public for the purpose of providing health care-related services. Hours of business must be sufficient to regularly serve patients. HHA context: CMS stated it will apply this requirement as applicable and does not interpret it to require an HHA administrative office to function as a public, patient-facing clinical site. |
| Public Visibility | Medicare beneficiaries must be able to contact and locate the provider’s or supplier’s location through publicly available information, such as the internet. |
| Permanent Signage | Providers and suppliers must maintain a permanent visible sign in plain view and post their hours of operation. – Building-complex rule: If located in a building complex, the sign must be visible at the building’s main entrance, or the provider’s or supplier’s hours may be posted at its own entrance. – Final exceptions: The requirement does not apply when the provider or supplier: – Shares office space with another provider or supplier, although a group practice itself must have signage; – Treats patients in their homes; – Treats patients in the provider’s or supplier’s home and uses that address only for administrative purposes; or – Furnishes telehealth services from home. CMS declined to treat a directory, website listing, shared/centralized sign, or compliance with State/local signage rules as an automatic substitute for provider-specific signage. CMS also declined a general cure period or materiality exception, while recognizing that it will consider atypical circumstances based on the facts. |
| Adequate Staffing and Resources | A provider or supplier must be properly staffed, equipped, and stocked, as applicable, to furnish its intended services or items. – Staff: Personnel must be qualified, including licensed or certified when State law requires it, to perform their health-care-related functions. – Equipment: Equipment must be functional, appropriate for the services or items the entity intends to furnish, and available in sufficient quantity. – Medications: Appropriate medications must be available in sufficient quantity when applicable to the services or items furnished. – Provider-specific application: CMS confirmed that an HHA is not expected to stock medications or equipment it does not lawfully dispense, own, or routinely furnish. |
| Operational Records and Policies | – Providers must have adequate written policies and records regarding operations, including procedures for patient care, patient safety, medical and patient recordkeeping, and general administration. – Records are required to be retained and furnished under 42 CFR § 424.516(f) must be accurate, complete, and compliant with all CMS requirements. This is limited to records covered by that retention provision and is not described as a new condition of payment. – CMS also retained discretion to consider other information when determining whether an entity is operational. State survey, accreditation, licensure, or other oversight status does not by itself establish compliance with these separate Medicare enrollment requirements. |
- Hospice Medical Directors and Administrators (§ 424.530(a)(20)) –
CMS finalized new § 424.530(a)(20) without modification, allowing CMS to deny a hospice’s Medicare enrollment application when its medical director or administrator cannot realistically carry out required hospice responsibilities, or when the medical director lacks the required active license. The finalized regulatory text reads as follows:
Hospice medical director or administrator. A hospice’s enrollment may be denied if any of the following apply:
(i) The hospice’s medical director is either of the following:
(A) The medical director of multiple other hospices.
(B) Practices at such a distance (for example, in a different state) from the enrolling hospice that the medical director cannot realistically perform all medical director functions required under 42 CFR part 418.
(ii) The hospice’s administrator is either of the following:(A) The administrator of multiple other hospices. (B) Located at such a distance from the enrolling hospice that the administrator cannot realistically perform all administrator functions required under 42 CFR part 418.
(iii) The hospice’s medical director does not have an active physician medical license in the State in which they are practicing.
CMS adopted this denial authority in response to hospice program-integrity concerns, including false terminal-illness certifications, kickbacks involving certifying physicians, administrators involved in criminal cases, and hospices billing while not meeting enrollment requirements. CMS specifically cited concerns where an individual directs numerous hospices, is located far from the hospice, or serves as a medical director with an inactive license.
The provision is designed to ensure that medical directors and administrators can provide meaningful oversight of hospice operations, quality of care, compliance with Medicare requirements, and beneficiary safety.
Key limits and clarifications
- No numerical cap: CMS did not set a maximum number of hospices a medical director or administrator may serve.
- No mileage or state-line rule: Physical distance alone does not automatically cause denial. CMS will assess whether the official can realistically perform all required functions.
- Limited, fact-specific use: CMS stated it expects to apply this authority only in limited cases after reviewing the full facts and circumstances. It declined to establish required factors, objective thresholds, or a mandatory investigation process.
- No rural/HPSA exception: CMS declined carve-outs for rural hospices, small hospices, health systems, or HRSA-designated Health Professional Shortage Areas.
- Only medical directors and administrators: The provision does not apply to system chief medical officers, regional medical directors, alternate administrators, or other leadership roles solely because of those titles.
- License location: The active physician license requirement applies to the state where the medical director practices, not necessarily the state where the hospice is located.
- Enrollment denials only: Section 424.530(a)(20) is a ground to deny an enrolling hospice. It does not itself create a revocation ground for existing hospices or alter hospice Conditions of Participation in 42 CFR part 418.
- No cure or phase-in period: CMS declined to provide a cure period for license lapses or a staged implementation period. CMS stated that significant arrangements could warrant denial beginning January 1, 2027.
If CMS denies the hospice’s enrollment under § 424.530(a)(20), CMS may impose a discretionary reapplication bar of up to 10 years because the final rule allows such a bar for a denial under any § 424.530 ground. The denial notice identifies the basis for any bar and its duration.
While the finalized policy does not ban shared or remote hospice leadership arrangements; it gives CMS case-specific authority to deny a new hospice’s enrollment when those arrangements prevent realistic performance of the medical director’s or administrator’s required duties, or when the medical director is not actively licensed where practicing.
- CMS Enrollment Form Revisions – CMS finalized its plan to revise three additional Medicare enrollment forms to collect whether disclosed organizational parties are private equity companies (PECs) or real estate investment trusts (REITs). CMS will add a checkbox to the following forms:
- Form CMS-855B — Clinics/Group Practices and Certain Other Suppliers
- Form CMS-855S — DMEPOS Suppliers
- Form CMS-20134 — Medicare Diabetes Prevention Program (MDPP) Suppliers
For each disclosed organizational owner, managing organization, or other applicable party, the supplier will indicate whether that party is a PEC or a REIT. The Forms CMS-855B and CMS-855S revisions will be submitted to OMB and will receive a 60-day public-comment period followed by a 30-day comment period.
DMEPOS Replacement Item Policy
CMS finalized updates affecting durable medical equipment (DME).
- A new order remains required, but a new face-to-face encounter is not required for an eligible replacement item with the same HCPCS code as the original item.
- Final rule: 42 CFR § 410.38(d)(2)(iii)
- CMS added the following clarification:
- “Replacement item” means an item identified by the same HCPCS code as the original item that has either:
- Been in continuous use by the same beneficiary and reached the end of its reasonable useful lifetime; or
- Been lost, stolen, or irreparably damaged.
- “Items ordered as replacement items do not require a new face-to-face encounter. All other requirements specified in § 410.38 continue to apply.”
What remains required
- A practitioner must issue a new order to reaffirm medical necessity for the replacement.
- The original face-to-face documentation must be retained and available to demonstrate that the initial item met applicable medical-necessity, billing, and coverage requirements.
- Other applicable coverage requirements, including National Coverage Determinations, Local Coverage Determinations, and item-specific practitioner-oversight requirements, remain in effect.
- Claims may still be subject to medical review.
Limits of the clarification
- It applies only when the replacement item has the same HCPCS code as the original item.
- A replacement product may be an updated technology, successor model, or newer generation if it remains within that same HCPCS code.
- A new face-to-face encounter is still required if the replacement involves a different HCPCS code, such as when a changed medical condition requires a different item or an added HCPCS item.
Expanded Coverage for Certain External Infusion Pumps and Home Infusion Drugs — CMS finalized an expansion of Medicare Part B DME coverage for certain external infusion pumps, associated home infusion drugs, and related supplies that previously could not satisfy the “appropriate for use in the home” standard.
- Effective April 1, 2027, an external infusion pump that meets the usual DME criteria may be treated as appropriate for use in the home even when professional administration or supervision is necessary, provided all of the following requirements are met:
- FDA labeling: The FDA-approved prescribing information for the associated home infusion drug instructs that it be administered by, or under the supervision of, a health care professional.
- In-home professional presence: The administration or supervision must be within that professional’s scope of practice under applicable federal and state law, regulations, and licensure requirements. The professional must be on site in the patient’s home; remote audio/video supervision does not qualify.
- Qualified supplier: A qualified home infusion therapy supplier, as defined at 42 CFR § 486.505, administers or supervises administration safely and effectively in the patient’s home.
- Infusion frequency and route/rate: FDA-approved labeling must instruct that the drug be infused at least 12 times per year, either:
- intravenously or subcutaneously; or
- at an infusion rate that the Secretary determines requires an external infusion pump.
- To support safe home infusion, CMS proposes that the supervising healthcare professional may be a registered nurse, clinical nurse specialist, nurse practitioner, physician assistant, or physician. CMS also proposes interpreting the “at least 12 times per year” requirement to mean at least once per month, reflecting typical drug dosing schedules.
Country-of-Origin Reporting Requirements – CMS finalized requiring suppliers participating in the DMEPOS Competitive Bidding Program (CBP) to report the country of origin for designated lead items furnished to Medicare beneficiaries. CMS describes this proposal as a transparency initiative intended to provide greater visibility into where certain DMEPOS products are manufactured.
- Who reports: DMEPOS Competitive Bidding Program (CBP) contract suppliers only, not all DMEPOS suppliers or all bidders.
- What is reported: The country of origin for each lead item reported on Form C, in addition to the existing manufacturer name, model name, and model number.
- Scope: Reporting is limited to the lead item in each product category. CMS declined to require country-of-origin reporting for non-lead items because of burden concerns.
- Timing: Suppliers submit Form C twice yearly, in January and July, during the CBP contract period, and must keep the information current when product information changes.
- Attestation: Form C will continue to require the supplier to attest that reported information is accurate and up to date.
- How suppliers determine origin: CMS expects suppliers to use the product’s country-of-origin marking, such as “Made in [Country].” If the item is exempt from marking, lacks a marking, or requires verification, the supplier may rely on manufacturer or distributor documentation, including certifications, bills of materials, manufacturing-process descriptions, commercial invoices, Customs entry records, or Harmonized Tariff Schedule classifications.
- Public disclosure and purpose: CMS will populate the reported country-of-origin data in the Medicare Supplier Directory during the contract period. The stated purpose is beneficiary-facing transparency, allowing beneficiaries and other interested parties to see where the lead item originated.
Enhanced Fraud, Waste, and Abuse Reporting – CMS finalized enhanced fraud, waste, and abuse reporting requirements for CMS-approved DMEPOS accrediting organizations (AOs) without modification.
Final requirement: 42 CFR § 424.58(c)(1)(xxiii)(N)
An AO must agree to:
“Notify CMS in writing (and, if applicable, law enforcement) of suspected fraud, waste, or abuse — consistent with the accrediting organization’s CMS-approved definitions of those terms … — within 3 calendar days of the date on which the accrediting organization determines that fraud, waste, or abuse may have occurred.”
Key elements
- Who must report: CMS-approved DMEPOS AOs, not DMEPOS suppliers directly under this provision.
- Reportable threshold: The AO determines that fraud, waste, or abuse may have occurred. CMS declined to raise this threshold or limit reporting to substantiated cases.
- Deadline: 3 calendar days, including weekends and holidays, from the date of the AO’s determination.
- Recipients: CMS in writing and, when applicable, law enforcement.
- Definitions used: The AO’s CMS-approved definitions of fraud, waste, and abuse, as required under § 424.58(c)(1)(xxii).
Related finalized changes
- AOs must report decisions to terminate, revoke, withdraw, or amend a DMEPOS supplier’s accreditation status to CMS within 5 calendar days. This replaces the prior 3-business-day deadline.
- AOs must disclose current conflicts of interest to CMS and explain how and when each conflict will be terminated.
CMS stated that prompt reporting supports proactive program-integrity oversight rather than a “pay and chase” response after improper payments occur. The DMEPOS accreditation revisions take effect 60 days after the rule is filed for public inspection.
Hospice Reactivations
CMS finalized a new requirement that a deactivated hospice obtain an initial State survey or accreditation before CMS can reactivate its Medicare billing privileges.
Final regulatory change
CMS revised 42 CFR § 424.540(b)(3)(i) by replacing “HHA” with “HHA or hospice.” The provision now requires an HHA or hospice whose billing privileges were deactivated under § 424.540 to obtain an initial survey or accreditation before reactivation.
CMS aligned hospice policy with the existing HHA reactivation rule. It concluded that a survey or accreditation provides an added safeguard that the hospice:
- Meets hospice Conditions of Participation;
- Is compliant with Medicare enrollment requirements;
- Is prepared to provide quality care; and
- Does not present program-integrity risk upon reentry to Medicare.
CMS emphasized that deactivated providers have halted billing privileges and are effectively seeking to reenter active Medicare billing. It cited heightened hospice program-integrity concerns as support for closer scrutiny.
Related reactivation provisions
- Reactivation effective-date rebuttal: A provider or supplier assigned a reactivation effective date may submit a rebuttal under § 424.546.
- Rebuttal deadline: The rebuttal must be submitted within 15 calendar days of the written notice date.
- Moratoria: CMS also finalized that reactivation applications count as “new” enrollments for temporary-moratorium purposes. Thus, a hospice seeking reactivation may be subject to a moratorium applicable to its type and geographic area.
- Estimated impact and effective date – CMS estimates that about 226 hospices annually seek reactivation. Using an estimated average survey or accreditation cost of $6,000, CMS projected annual costs of approximately $1.356 million for reactivating hospices. The provider-enrollment change takes effect 60 days after the final rule is filed for public inspection.
Palliative Care Services as Home Health Services
CMS finalized a clarification—not a new benefit—that palliative care may be furnished under the existing Medicare home health benefit when it is part of a covered skilled service, and all home health eligibility requirements are met. CMS did not finalize a palliative-care carve-out, separate palliative track, or new palliative-specific measure in this rule.
- What CMS finalized
- No new palliative-care benefit or payment pathway. CMS did not establish a new service category, separate billing code, add-on payment, distinct service-delivery model, or new palliative-care eligibility criteria.
- Existing coverage can include palliative care. A beneficiary can receive palliative-care-related home health services when the individual qualifies for the home health benefit and the services are ordered by a physician or allowed practitioner, included in the individualized plan of care, and meet the skilled-service standard.
- All existing eligibility requirements remain. These include homebound status, a qualifying skilled need, an order by a physician or allowed practitioner, an established plan of care, and the required face-to-face encounter.
CMS reiterated that a service can be skilled when it is inherently complex enough to require professional or technical personnel, or their supervision. Coverage depends on the patient’s individual condition, needs, care goals, and accepted medical and nursing practice.
Importantly, skilled care may be reasonable and necessary even when the illness is chronic, terminal, or not expected to improve. Medicare does not require the avoidance of life-prolonging therapies, and lack of recovery potential does not by itself preclude coverage. Skilled services may be covered to prevent deterioration or preserve current capabilities.
- Examples CMS recognized
Within the existing home health benefit, palliative-care-related skilled services can include:
- Skilled nursing: advanced pain and symptom management; management of nausea, vomiting, anxiety, depression, or respiratory distress; medication monitoring and coordination of medication changes.
- Patient and caregiver education: teaching and training on managing symptoms and treatment responses at home.
- Medical social services: advance-care-planning needs, including discussion of possible hospice transition, and referrals for emotional and social support for patients, families, and caregivers.
- Therapy services: non-pharmacologic pain-management strategies, mobility and safe transfers, adaptation of activities of daily living and the home environment, safe eating and drinking, communication, and decision-making support.
CMS said palliative services will often fit most naturally within the PDGM medication, management, teaching, and assessment (MMTA) clinical group, but clarified that they may be provided across all home health disciplines and according to the care plan.
- Documentation and payment
- Clinical documentation must support the specific skilled need, the goals in the plan of care, the skilled interventions provided, and the patient’s progress toward care needs and goals.
- HHAs continue to bill under existing home health billing and coverage rules. Palliative-care activities must fall within a covered skilled service; they are not separately billable merely because they are palliative in nature.
- CMS plans to update Chapter 7 of the Medicare Benefit Policy Manual with additional examples of skilled palliative care and to provide MAC instructions and education intended to promote consistent medical review and reduce avoidable audit or claim-denial barriers.
- Homebound, hospice, and practitioners
- Homebound status: Existing rules apply. A patient can remain homebound when absences are infrequent or short, or are for health-care treatment, even where leaving home requires a considerable and taxing effort.
- Not a substitute for hospice: CMS emphasized that home health and hospice remain distinct but complementary benefits. Home health palliative care can support people with serious illness, including those who have not elected hospice, without replacing the hospice benefit’s more intensive interdisciplinary model.
- Allowed practitioners: Nurse practitioners, physician assistants, and clinical nurse specialists may certify eligibility and establish the home health plan of care, consistent with the definition of allowed practitioner.
- Quality measurement considerations
CMS agreed that functional decline can be clinically expected for patients receiving palliative care and is not necessarily poor quality. In discussing possible future alignment of the HH QRP and expanded HHVBP Model, CMS stated that measure sets will emphasize expected functional outcomes, including whether a patient is expected to improve, maintain, or decline, rather than focusing only on improvement.
Table of each finalized decision discussed and its effective date.
| Final decision | Citation | Effective date |
| Palliative care may be furnished under the existing home health benefit when part of a covered skilled service | Preamble clarification (no new reg text) | 60 days after Federal Register filing (estimated Dec 28, 2026) |
| Hospice medical directors and administrators — new enrollment denial ground | 42 CFR § 424.530(a)(20) | Jan 1, 2027 |
| Operational definition updates (incl. qualified physical practice location, accessibility, staffing/resources, policies/records) | 42 CFR § 424.502 | Jan 1, 2027 |
| Permanent signage requirement (provider/supplier signage and posted hours; specified exceptions) | 42 CFR § 424.510(f) | Jan 1, 2027 |
| Change in Majority Ownership (CIMO) noncompliance — denial/revocation for HHAs, hospices, DMEPOS | 42 CFR §§ 424.530(a)(22), 424.535(a)(25) | Jan 1, 2027 |
| Reduced claims-submission window after revocation (15 calendar days from letter date) | 42 CFR § 424.535(h) | 60 days after filing (estimated Dec 28, 2026) |
| Hospice reactivations require State survey or accreditation before billing privileges can be reactivated | 42 CFR § 424.540(b)(3)(i) | 60 days after filing (estimated Dec 28, 2026) |
| DMEPOS replacement items: same HCPCS code does not require a new face-to-face encounter (new order still required) | 42 CFR § 410.38(d)(2)(iii) | 60 days after filing (estimated Dec 28, 2026) |
| DME Part B coverage expansion for certain external infusion pumps/drugs/supplies (when professional is on site) | 42 CFR § 414.202 (revised DME definition) | Apr 1, 2027 |
| Enrollment forms: add PEC/REIT checkboxes to CMS-855B, CMS-855S, CMS-20134 | PRA process (no reg date) | Upon OMB approval and form release (date TBD) |
| CBP country-of-origin reporting for lead items on Form C (contract suppliers) | PRA process; Supplier Directory posting | Next CBP contract period; no earlier than Jan 1, 2028 |
| DMEPOS accrediting organizations must report suspected FWA within 3 calendar days; report accreditation status changes within 5 calendar days | 42 CFR § 424.58(c)(1)(xxiii)(N) and related AO provisions | 60 days after filing (estimated Dec 28, 2026) |
Note:
- “60 days after filing” is based on approval Oct 28, 2026, and scheduled publication Nov 9, 2026, yielding an estimated effective date of Dec 28, 2026, for provisions tied to the general effective-date clause.
- HH PPS/HH QRP/§ 484.245 provisions have Jan 1, 2027, effective dates per the rule’s DATES section; enrollment items listed above are shown as Jan 1, 2027, where CMS specified that date in the preamble; other enforcement items follow the 60-day clause where CMS stated so in the final text/preamble.
Review the final rule on the Federal Register Public Inspection desk
For further information, see the CMS Fact Sheet of the HHA final rule
Questions about the content of this rule? Contact CHAP